New Blood Test Detects Dozens of Cancers Early
A simple blood draw could now catch more than a dozen different cancers. This breakthrough includes spotting diseases that currently lack standard screening guidelines or are frequently found too late for effective treatment.
Researchers recently analyzed data from nearly 36,000 people using this new method. The test functions much like a routine outpatient visit and successfully picked up cancer signals across 17 distinct types. These included ovarian, lung, breast, and colorectal cancers among others.
The multi-cancer early detection tool looks for tiny DNA fragments that cells release into the bloodstream. Among all participants tested, 287 received a positive result. Doctors then diagnosed actual cancer in 173 of those individuals.
Overall accuracy shows about six out of ten people with a positive test actually have cancer. This gives the test a positive predictive value of 60.3 percent. Conversely, it correctly ruled out cancer for nearly everyone who did not have it. That figure hits an impressive specificity of 99.6 percent.
When the test identified cancer correctly, it pinpointed the specific origin in about 91 percent of cases within its top two guesses. Many of the cancers found were types without official screening recommendations at all.
Dr Karthik Giridhar from Mayo Clinic led this research effort as a senior author. He noted that most cancers lack established screening tests today. This study helps clarify how blood tests can fill gaps left by routine methods to find signals otherwise missed.
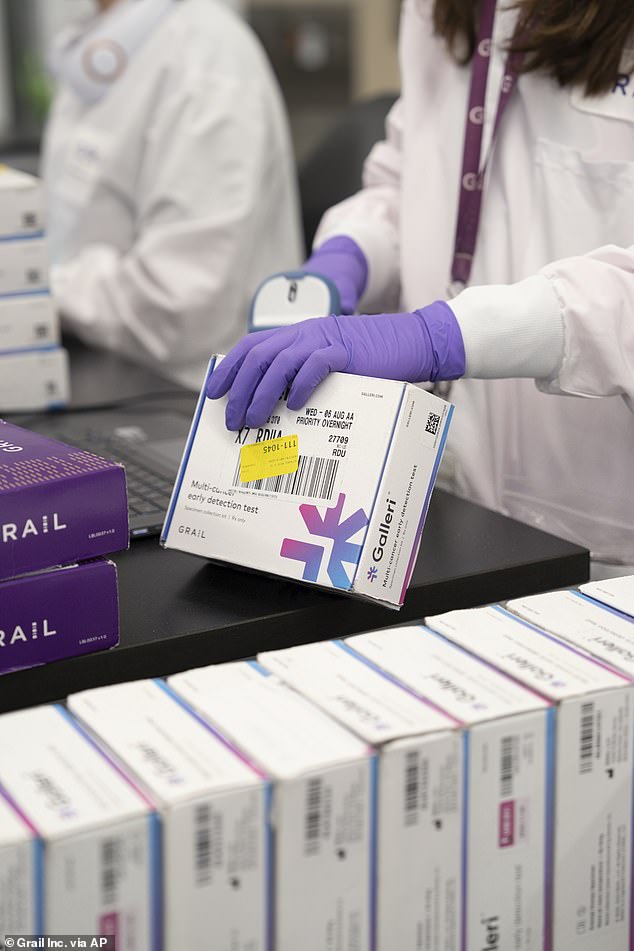
The Galleri MCED test being evaluated is an earlier version developed by GRAIL. It detected conditions ranging from anal and bladder cancer to skin, stomach, and thyroid varieties. The full list also covered lymphoid, myeloid, pancreatic, gallbladder, and fallopian tube cancers.
Of the 151 participants with newly diagnosed cancers found by the test, 53 percent had stage 1 or 2 disease only. A staggering 71 percent had caught cancer at stages one through three combined. This early detection matters greatly for survival rates.
Only breast, colorectal, and lung cancers currently hold a USPSTF grade A or B recommendation for screening. The US Preventive Services Task Force sets these grades based on expected benefits. Grade A means substantial benefit with high certainty. Grade B covers moderate benefit or high certainty of moderate to substantial gains.
Clinicians should offer these specific tests to eligible patients under current guidelines. Breast cancer gets a mammogram check. Colorectal screening involves colonoscopies or stool and imaging tests. Lung cancer screening relies on low-dose CT scans.
The other 14 cancers without official recommendations still need monitoring strategies tailored to individual risks. Screening varies based on lifestyle choices, family history, and medical background. High-risk groups like people with HIV might get anal Pap tests for anal cancer. Doctors use visual exams and hands-on checks for head and neck issues.
This technology offers a new path forward where standard tools fall short. Communities face fewer missed diagnoses if these blood draws become widespread. Early identification changes outcomes dramatically for patients who slip through the cracks today.
Some cancers like ovarian and fallopian tube types remain elusive because current screening methods for average-risk women have not shown enough benefit to justify routine checks for everyone. Transvaginal ultrasound and specific blood tests simply haven't produced the evidence needed to support population-wide screening. Consequently, these diseases often slip through until they reach later stages, spreading to other body parts where treatment becomes far more difficult.
While the MCED test shows promise, Giridhar points out it is not a replacement for established screenings yet. Instead, it should supplement existing approaches and help experts learn more about detecting cancer. The MCED tested in this research was an earlier version of GRAIL's Galleri MCED test. That specific product has been replaced by the current version available today.
Galleri is now sold in the US via prescription from a doctor, but it is not yet FDA-approved. The agency is still reviewing the application. On Wednesday, an FDA advisory committee voted 7-2 that the test's benefits outweigh its risks. Right now, the test targets adults at elevated cancer risk and costs $949.
The study was funded by GRAIL, the company behind Galleri. Several authors reported financial ties to the firm through employment, stock ownership, or consulting roles. This connection raises questions about potential bias, yet the committee still moved forward with approval based on available data. Communities relying on early detection must wait for final FDA action before widespread use begins.
Photos