Immunotomy Saved My Life but Left Me With Mystery Illness
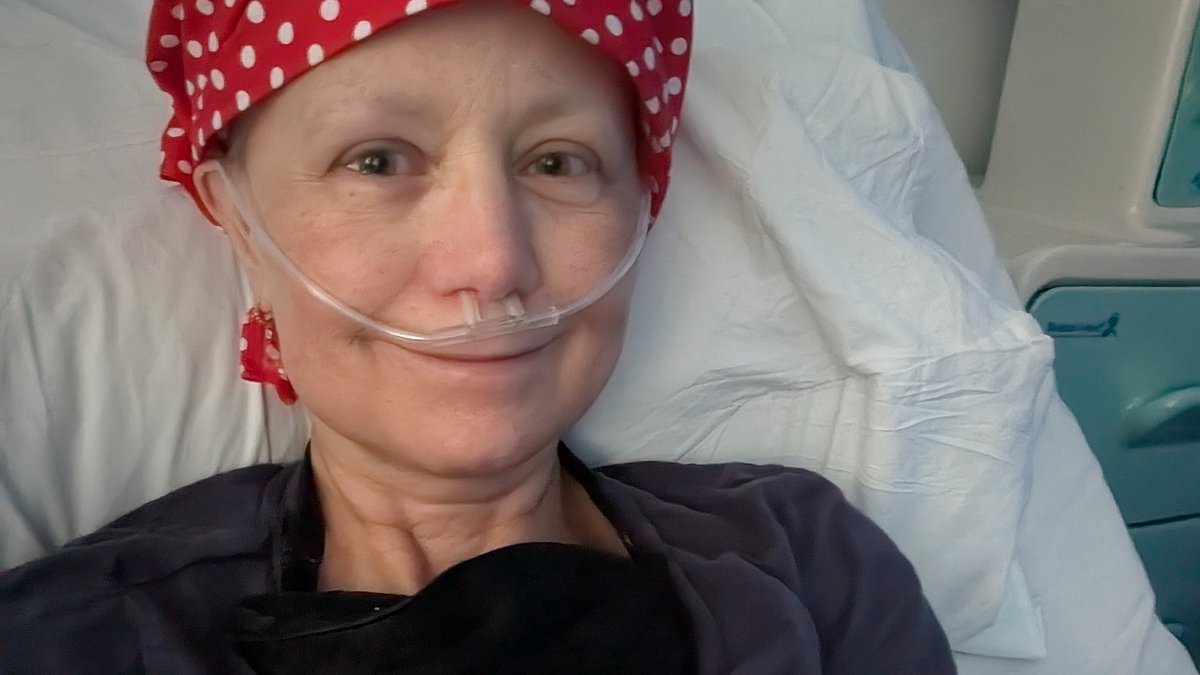
Immunotherapy was meant to be a miracle cure, yet it saved one woman's life while condemning her to a lifelong battle with a mysterious illness. Is this revolutionary treatment truly worth the risk for millions now receiving it? My surgeon looked at me with a kind face that hid nothing as I sat there waiting for his verdict on my operation. He knew exactly what he was about to say would define my future, just as I did. Finally, he smiled and told me the pathology report was clear. All cancer cells were gone. It was the best possible outcome. My partner, Richard, hugged me before those words fully registered in my mind. The previous eight months had been the hardest of my life because I endured grueling treatment for an aggressive form of breast cancer. Before that surgery, I completed fourteen rounds of chemotherapy alongside immunotherapy. This newest cancer treatment harnesses the body's own immune system to hunt down and destroy malignant cells. It worked. But as the fear of death finally began to lift, I realized my extraordinary news came at a steep price. The therapy turned my immune system against my own flesh, leaving me with life-threatening and potentially long-lasting side effects. As I discovered, a super-charged immune system does not have an off-switch. Even though my last dose was administered seventeen months ago, I am still living with these effects today. New research shows I am far from alone in this misery.
Immunotherapy has been hailed as revolutionary for good reason. Introduced less than two decades ago, it transformed the outlook for cancers once thought almost impossible to treat. The most dramatic example is advanced melanoma, the deadliest form of skin cancer. Until little more than a decade ago, fewer than five percent of patients survived ten years after diagnosis. Today, thanks to immunotherapy, more than half survive that long, and some are considered cured. This is an astonishing turnaround that many specialists once deemed impossible. Similar breakthroughs have followed in certain forms of lung and kidney cancer. Researchers are also seeing encouraging results in pancreatic cancer and other notoriously difficult tumors. Hopes are rising that this success story is only just beginning. But as I discovered first-hand, this extraordinary treatment carries a cost. Patients often develop side effects caused by their immune system attacking healthy tissue. Some, like me, are left with health problems that persist long after therapy ends. The most frightening part is that it is impossible to predict who will develop these complications or which organ the immune system will strike.
I was the fittest I had ever been when diagnosed with cancer. At age fifty-six, I ran three times a week, had been a vegetarian since my teens, did not smoke and drank in moderation. I had even written books about health. I found the lump in my right armpit in November 2024 during my regular breast self-check. I reassured myself because it was not in my breast so it was probably nothing. It wasn't nothing. A month later, after scans and a biopsy, I heard the words we all dread: You have cancer. Not just any breast cancer, but triple negative breast cancer. This is a rarer, more aggressive form that is harder to treat because it lacks the receptors targeted by many of the most effective drugs. The lump in my lymph node had grown to the size of a Brussels sprout. It was an irony not lost on me: I received my diagnosis just before Christmas. Stranger still, doctors could not find the original tumor in my breast. The treatment was almost as frightening as the diagnosis itself. I faced six months of chemotherapy followed by surgery and radiotherapy.
Even then, there were no guarantees. In clinical trials, around one in four women like me who received standard treatment alone saw their cancer return within three years. But there was one reason to hope. Just two years before my diagnosis, the NHS had approved pembrolizumab, an immunotherapy drug, for patients like me. It belongs to a new generation of treatments that work by taking the brakes off the immune system, allowing it to recognise and attack cancer cells that would otherwise slip under the radar. My oncologist was candid about the risks. By unleashing the immune system against the cancer, the drug could also cause it to attack healthy organs. My thyroid was one possibility. My lungs, liver, bowel, skin or heart could also be affected. I could say no.
But knowing the poor prognosis women with TNBC face, I wanted to throw everything at the tumour. Besides, I was already signing chemotherapy consent forms listing scores of nasty complications. A few more seemed the least of my worries. I said yes. Treatment started the day before Christmas Eve. It wasn't pleasant, but side effects such as nausea were mostly controlled by the party bag of medications I received after my weekly infusions. I wore an icy 'cold cap' to try to save some of my hair, and tried to keep walking the dog and working.
But overnight in early March everything changed. I developed acute diarrhoea, up to 14 times a day. As I got weaker, my consultant diagnosed colitis – inflammation of my large intestine. My immune system was attacking my digestive system. Colitis can be life-threatening, so I spent every day in the emergency department receiving high-dose steroid infusions, along with other specialist medications. I'd undergone 14 rounds of chemotherapy alongside immunotherapy – one of the newest cancer treatments available, which harnesses the immune system.

After decades of healthy eating, I had to ditch my five-a-day for what is known as a low-residue diet – low in fibre to reduce the amount of work my damaged bowel had to do – consisting of white bread, jacket potatoes and the occasional banana. The cancer treatment had to stop completely while the oncology team tried to calm down my fiery immune system. It took a month for the treatment to kick in and ease my symptoms, and the steroids left me so wired I couldn't sleep. When insomnia struck, I'd lie awake researching the condition for the blog I'd started after my diagnosis. I wanted to understand what had happened to me. The answer lay in something known as immunotherapy toxicity.
By revving up the immune system to attack cancer, immunotherapy can also cause it to attack healthy parts of the body – as I'd been warned. But what I hadn't fully grasped was that unlike chemo, where side effects are unpleasant but usually short-lived, immunotherapy toxicity can flare up years after treatment. Professor Richard Simcock, chief medical officer at Macmillan Cancer Support, explains: 'One of the hardest aspects of immunotherapy toxicity is its unpredictability. We don't yet have a way of understanding who will be affected, what side effects they may get and, crucially, how long problems may last.' All of this massively contributes to the uncertainty.
I had to stop pembrolizumab after just three doses instead of the planned 17, but I was able to restart chemotherapy. By June, I could no longer climb the stairs without stopping to catch my breath, and I'd developed a relentless dry cough. One night, after a blood transfusion, my temperature soared and I struggled to breathe. We called 999 and, within minutes, I was in an ambulance, blue lights flashing as we raced to A&E. I was given an oxygen mask as doctors tried to work out what was wrong. Antibiotics made no difference – I was getting sicker by the hour. My chest felt as though it were being crushed in a metal vice. Too frightened to sleep, and convinced I was dying, I searched my symptoms online.
Pneumonitis was the enemy. My own super-charged immune system turned on my lungs. Forty-eight terrifying hours passed before a specialist toxicity team began pumping huge doses of IV steroids into me. Within hours, breathing became easier again. By day two, I could manage without oxygen support.
Surgery got delayed while my lungs healed. Then came the best news of my life at the end of July: there was no sign of cancer left. It is impossible to say which of the five medications killed off the tumour, but that night I toasted the team and the chemo and the pembrolizumab.

My immune system had not quite finished with me yet. As soon as I stopped taking steroids, my colitis returned with a vengeance, ruining plans for an August spent enjoying recovery. The saving grace was the fantastic immunotherapy toxicity team in Sussex. Expert nurses delivered more steroid infusions and kept morale high enough for me to finally have radiotherapy.
Severe joint pains followed, probably caused by steroids weakening muscles. I started gentle physio and drank every protein smoothie I could stomach. By January of this year I felt 96 years old instead of 56. The pain spread to my hips, knees, wrists, elbows, even my heels.
Could the immune system have found a new target? Sure enough, restarting steroids made the pain improve overnight. This confirmed a diagnosis of inflammatory arthritis. Steroids are not a long-term solution though. I can live with the swollen moon-face they cause, but the reduced immunity means I catch every bug going around.
Doctors want to find an alternative because some newer treatments are not available on the NHS. For now I am trying another drug that leaves me nauseous and dog-tired three days out of seven. If that fails, I may get compassionate funding for more expensive meds.
At first I assumed bad luck was to blame. Now we know that wasn't it. The biggest study in Europe followed 545 patients who had the same treatment across 34 UK hospitals. Two-thirds suffered an immune-related side effect. Nearly half needed unplanned stays in hospital. Four patients died, including three whose lungs were attacked by pneumonitis.
Professor Anna Olsson-Brown set up the team that treated me. She is chief executive of the Immuno-Oncology Clinical Network and chair of the UK Society for Medical Oncology. She says severe or life-threatening toxicity affects somewhere between one in five and one in two patients, depending on the treatment. Many are left with long-term, life-altering symptoms. With 25,000 patients treated with immunotherapies last year in England alone, these toxicities are not a rare complication. They are a routine part of the treatment.
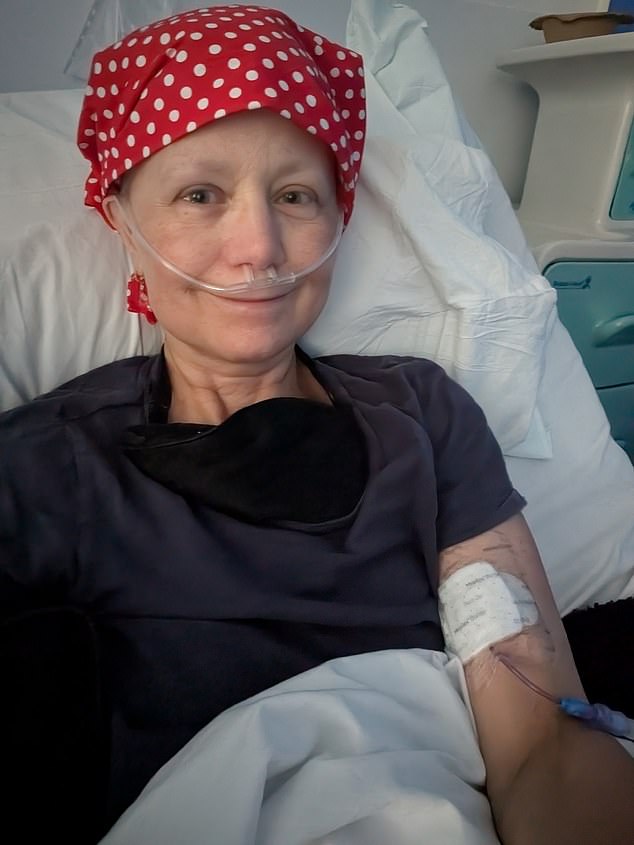
The effects go beyond individual patients. The list price for a full course of pembrolizumab is nearly £90,000, though the NHS gets a discount. Emergency admissions, specialist drugs, and years of follow-up add to the burden on struggling cancer units. I was lucky to have access to a specialist team, but these services are few and far between.
Doctors talk about a golden age of cancer care thanks to treatments like immunotherapy. But I have learned we need to choose what is right for us. Always ask to have the effects explained more than once or to see the research. You must be your own champion. Non-specialist medics do not always understand immunotherapy side effects, but it is your body and you have the right to be taken seriously.
During sleepless nights when a cocktail of pills or joint pains keep me awake, I relive those terrifying times in A&E. Did I make the wrong decision agreeing to immunotherapy? Deep down I know I would still say yes. It was very likely it helped get rid of my cancer, just as it has for tens of thousands of people.
The sting in the tail remains a persistent worry for many patients, even as medical teams search for better treatments. I just hope that medics also discover new ways to treat the sting in the tail. This pain can linger long after the primary treatment is over, leaving sufferers with no easy answers.
On another front, Kate's blog, My Big Cancer Plot Twist, stands ready to help anyone touched by this disease. The site includes advice and links for anyone affected by cancer, offering a lifeline of information when it matters most. It provides real support in times of need.
Photos