DRC Battles Worst Ebola Outbreak as Bundibugyo Strain Spreads

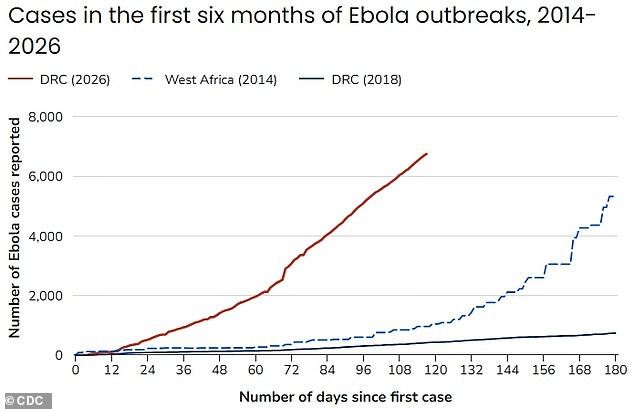
A critical moment has arrived in the battle against Ebola within the Democratic Republic of the Congo. The nation now faces a stark choice: accelerate its efforts to contain the virus or watch it evolve into the deadliest epidemic ever recorded in history. Since May 2026, when officials first declared the outbreak, more than 6,186 confirmed cases and 3,007 deaths have been logged as of September 1. These grim numbers mark the worst Ebola crisis to strike the DRC.
The culprit is the Bundibugyo strain of the virus. Unfortunately, no licensed vaccine or specific treatment currently exists for this particular variant. The infection likely began in late April 2026 inside the bustling mining region of Mongbwalu in Ituri, located in north-eastern DRC. From there, it hitched a ride through interconnected communities and healthcare networks, reaching Rwampara and Bunia within Ituri province before crossing into Uganda.
The government of the DRC leads the charge, backed by partners like the Africa Centres for Disease Control and Prevention, the World Health Organization, and others. They are working to expand surveillance, boost lab capacity, set up treatment centers, enforce infection control rules, distribute vaccines, manage logistics, engage with communities, and ensure safe burials. In Uganda, decisive national leadership helped cut off transmission entirely after close cooperation with locals.
Yet in the DRC, progress remains uneven. Insecurity, heavy population movement, late detection of cases, funding gaps, supply shortages, and a lack of community ownership keep the virus alive. Experts warn that the current response is insufficient to stop spread within the country. The fight must move closer to the village level, bringing testing, treatment, vaccination, and engagement directly to where people live.
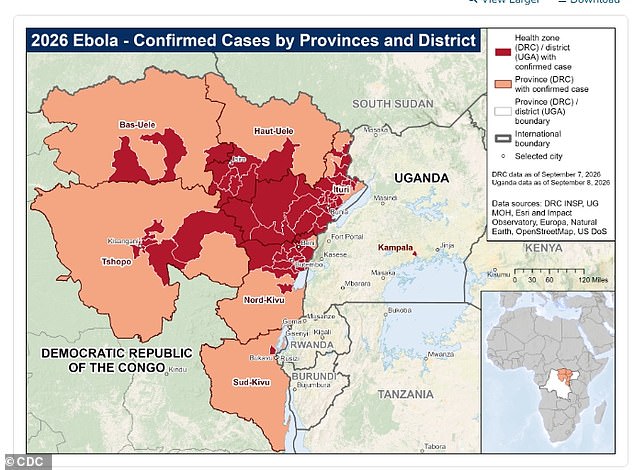
Public health specialists point to four specific hurdles driving this nightmare scenario. First, the environment itself is a barrier. Affected zones are vast, remote, and often dangerous. A short trip can take a full day or more on crumbling roads, especially during the rainy season which is currently in session. Second, people move constantly. Mining towns, motorcycle taxi routes, displaced families, and cross-border travelers link villages that are hard to monitor. Bunia serves as a major hub connecting these transmission hot spots.
Third, trust remains fractured. When fear grips a village, when clinics shut down after health workers die, or when families suffer without seeing action, people delay seeking help. This directly blinds surveillance systems. Recent investigations suggest many cases slip through the cracks because they are identified outside official contact lists. Finally, the scientific arsenal is incomplete for the Bundibugyo virus. These four factors combine to make control nearly impossible right now.

The current situation proves that relying solely on traditional contact tracing will not suffice. Unlike the Zaire species which causes Ebola, this Bundibugyo virus lacks a licensed vaccine or specific treatment options right now. Consequently, clinical research has become an essential part of the response effort itself. The Democratic Republic of Congo has already begun vaccination campaigns in Kisangani for health workers and frontline responders who face the highest risks. Over 50,000 doses have arrived so far while the International Coordinating Group on Vaccine Provision approved 70,000 doses of Ervebo for national use. Approximately 20,000 of those will be reserved for a clinical trial to gauge effectiveness against this specific strain.
Significant progress has occurred in just three months between May 15 and August 15, 2026. More than 20 Ebola treatment and isolation facilities have been established or supported during this period. Treatment capacity was overwhelmed in late May with bed occupancy exceeding 200 percent before the crisis peaked. By late August that number had dropped to around 66 percent as conditions stabilized. Laboratory capacity has expanded dramatically too, with 22 labs now operating across five affected provinces instead of just one in Kinshasa. This shift reduced turnaround time from over a week to mere hours between sample collection and results. Safe and dignified burials have improved substantially, with the vast majority taking place within 24 hours now.
Encouraging epidemiological signals confirm these operational gains are working. The effective reproduction number has fallen substantially from very high levels observed in May when each infected person passed Ebola to four others. That average infection rate has dropped from four down to just over one per patient. The scale of resources mobilized for this outbreak remains substantial with approximately 1.72 billion dollars in pledges including 118.5 million committed by African countries. Around 867 million dollars, which is about half the pledges, has reportedly been released already. A continental response plan launched on June 5, 2026 by Africa CDC and WHO was built around a simple principle of one plan, one budget, one team, and one monitoring framework with communities at the center.
The next phase must shift focus directly to villages where local representatives, health workers, and leaders should become active partners in surveillance and early detection. Digital tools can support these efforts but technology must serve the community rather than replace genuine human connection. Commercial motorcycle riders who connect communities across enormous distances must be engaged as partners instead of being treated simply as a risk factor. Vaccination needs to move closer to remote communities where people actually live. Research must happen right where the epidemic is occurring without delay. Clinical trials for vaccines and therapeutics must proceed with urgency and scientific rigor at every step. Essential health services must continue alongside Ebola control measures rather than competing with them. The same logic applies when reopening schools since education cannot wait indefinitely while we fight this disease.
Stopping infection requires more than just medicine; it demands strict prevention measures. Teachers need proper training. Schools must have hygiene facilities. Clear referral mechanisms must be developed. Communication about the epidemic has to adapt for children and families. These steps are non-negotiable.

Humanitarian aid and Ebola responses cannot run on parallel tracks. A community already dealing with insecurity, displacement, and disease cannot manage separate systems for each crisis. That is not a realistic expectation. The DRC-Uganda collaboration shows how regional solidarity actually works. It means joint surveillance. Diagnostic capacity moves closer to border communities. Information gets shared. Action stays coordinated across the region.
Ebola does not respect borders. Lessons from the DRC and Uganda must spread now. They need to reach South Sudan, the Republic of Congo, and other neighboring countries. This extension was agreed upon in Bangui, Central African Republic, back in mid-August. Time is running out. We cannot wait any longer.
Photos